Bureau theme
Healthcare

Patient access.
Urgency before intent.

Most patient contact is administrative: booking, rescheduling, directions, preparation instructions, form completion. A small proportion is not, and the entire design problem is reliably telling the two apart.

THE ASYMMETRY

In most support contexts a wrong answer costs a customer some inconvenience. In patient access, the distribution of consequences is extremely uneven: nearly every interaction is harmless to get slightly wrong, and a very small number are catastrophic. A system designed around average performance is designed around the wrong statistic entirely.

So the architecture is built around the tail. The first question the system answers is not what the patient wants, but whether this contact shows any indication of urgency — and the threshold for handing to a human is set deliberately low, accepting a substantial rate of unnecessary escalations as the cost of the safety property.

That is an unusual thing to optimise for and it needs saying to a client early, because it means the automation rate will be lower than a vendor promising eighty per cent deflection will quote. We think a lower deflection rate with a safe failure mode is the only honest product in this setting.

WHAT IT HANDLES
01

Scheduling and rescheduling

Booking against real availability, handling cancellations, managing waiting lists and filling slots freed at short notice — which is where a meaningful amount of unused clinical capacity actually sits.
02

Preparation and logistics

Fasting instructions, what to bring, where to park, how to get there, what happens on the day. High volume, low risk, and consistently the largest share of inbound contact.
03

Intake and forms

Structured collection before an appointment, validated as it is entered, so a clinician opens a complete record rather than chasing a missing item during the consultation.
04

Not: clinical advice

Any contact touching symptoms, medication, deterioration or distress goes to a human, immediately, with the full conversation attached. The system does not triage clinically and does not attempt to reassure.
HOW WE VALIDATE IT

The evaluation set is built primarily from the dangerous cases, not the common ones. Real contacts where urgency was present but the opening words looked administrative — the caller who asks to rebook and mentions chest pain in passing. Performance on that set is the gate; performance on routine booking is assumed and monitored.

Escalation is logged with the reason, and sampled by clinical staff on an ongoing basis. Two numbers are watched: how often it escalated unnecessarily, which is a cost, and whether it ever failed to escalate when it should have, which is not a cost but a stop.

And the system says what it is. Patients are told they are talking to an automated service and how to reach a person, in the first exchange. Beyond being required in many places, it materially changes how people phrase things — and in this setting that is a safety feature.

HOW A CONTACT IS ROUTED
CONTACT PATH
  1. Patient contact
    call, message or web
  2. Urgency screen
    runs first, threshold set low
  3. Identify
    patient and appointment context
  4. Resolve
    booking · preparation · intake
  5. Confirm
    written back to the PAS
  6. Human, immediately
    any hint of clinical urgency
Solid: the administrative path Dashed: escalation, with the full conversation attached
Urgency is evaluated before intent. The escalation threshold is deliberately conservative, which lowers the automation rate on purpose.
QUESTIONS
QUESTIONS — 3

Lower than a general-purpose support vendor will quote, because the escalation threshold is deliberately conservative. We would rather set that expectation at the outset than hit a target by weakening the safety property. The right measure is administrative contacts resolved without a person, not total contacts.

Clinical triage is a clinical activity and in many jurisdictions a regulated one. This system detects possible urgency and routes to the people who triage. It does not assess severity and does not advise.

It has to — availability, booking rules and patient identity all live there. That integration is usually the larger part of the build, and it is the part where the realistic timeline is set.

Keep reading
30-minute technical call · no deck

Design for
the tail.

Average performance is the wrong statistic when a small fraction of contacts are urgent.

CASE STUDIES

Shipped work.
Go and check it.

The work we can name, with the live site, our scope and the boundary made explicit. Select a project to see the evidence; each is a full case study, not a logo or a claim.

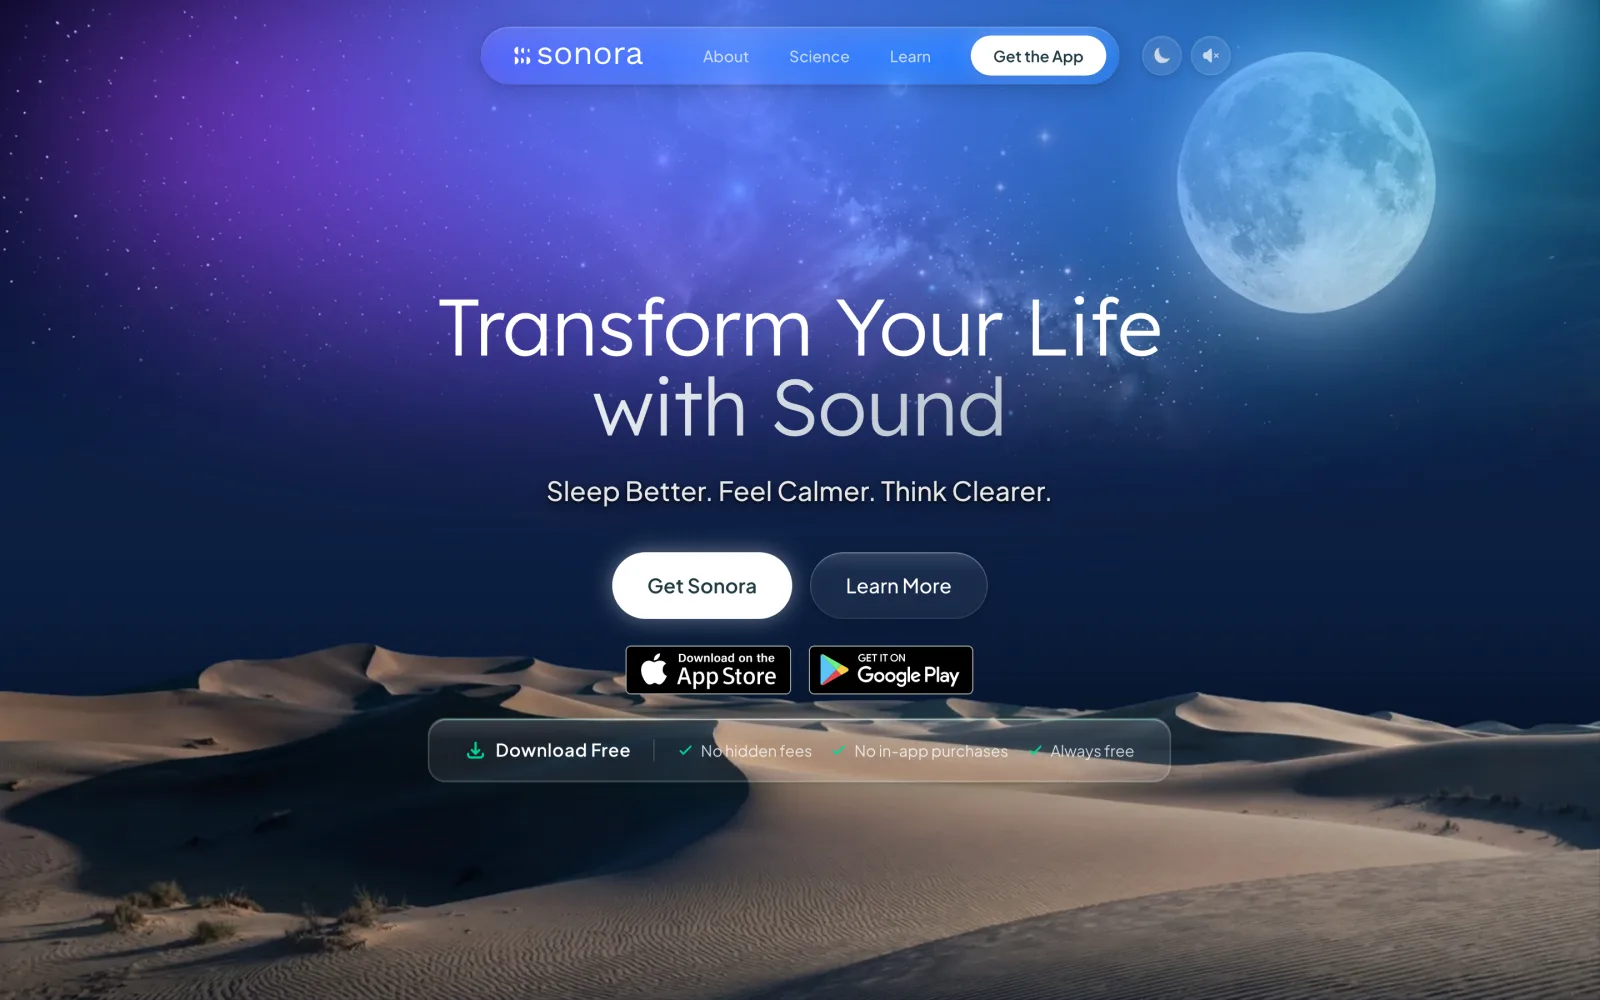
sonora.com
The Sonora homepage on desktop: a full-bleed dune landscape behind the headline “Transform Your Life with Sound”, with App Store and Google Play download buttons.
sonora.com — homepage, 1440×900 sonora.com →
Live Consumer wellness · Mobile + web

Sonora

Cognitive AI Ltd · 2026

A free sound-wellness app, described by its publisher as AI sound therapy that reads a short vocal sample at the start of a session and generates a soundscape for that moment. We designed and built the website and its backend, produced assets for the iOS and Android apps, and supported the application prototype.
Read the case study →

See every published project →

WHO WE HAVE BUILT FOR

Twenty-one years of applications, platforms and campaigns for names you know.

See all of our work →



















