Bureau theme
Industry

Healthcare AI,
inside your perimeter.

Documentation, trial evidence and patient access — built to GDPR Article 9-aligned controls, on infrastructure inside your own perimeter. A clinician stays accountable for every record.

Maker protecting clinical records within a care perimeter
Last reviewed 4 September 2026 · Engineering guidance, not legal or regulatory advice.
WHERE IT BREAKS TODAY
01

Unstructured by default

Patient charts, trial reports, claims and the literature arrive as prose and PDF. Most of what a clinical or research team needs is in there; almost none of it is in a form a system can act on.
02

Documentation competes with care

Documentation burden is one of the most consistently cited contributors to clinician burnout, and it is work that competes directly with patient care and with research.
03

The data cannot go to a public endpoint

Off-the-shelf tools without a business-associate agreement (US) or a lawful basis and processor terms for special-category data (EU, GDPR Article 9) cannot be used on patient data — so most clinical workflows stay manual.
OUR APPROACH

Reducing administrative burden

The systems we build in healthcare share one design rule: the model changes how long the administrative work takes, not who is accountable for it. A note is drafted, but a named clinician reads and signs it. A trial value is extracted, but it carries a citation to the page it came from. A patient contact is resolved, but any hint of clinical urgency goes to a person first.

That rule is what keeps the work on the right side of the medical-device boundary. A system that suggests a diagnosis or assesses severity is a medical device in most jurisdictions, with a regulatory pathway to match. We build the administrative layer around the clinical one, and we say clearly where the line is. Whether a given system crosses it is for your regulatory function to determine.

HOW IT DEPLOYS
PHASE 01

Map the workflow

We audit clinical and administrative data flows — EHR entries, claims, trial documentation — and identify the highest-burden extraction and routing targets.
PHASE 02

Deploy inside the perimeter

Models run on infrastructure you control, designed so that PHI does not leave your perimeter — controls enforced by the architecture, not only by policy.
PHASE 03

Return time to care

Extraction, drafting and routing are handled by the system; review and signature stay with a clinician, and every routed record carries a full audit trail.
WHAT WE BUILD
01

Clinical Trial Data Extraction

Multimodal models that extract cohorts, adverse events and efficacy measures from PDF trial reports into a reviewable table, with a citation on every value so a researcher can verify it at source.

SEE RAG SYSTEMS →
02

Patient Access Automation

Scheduling, preparation instructions, intake and forms, with any indication of clinical urgency routed immediately to a person. The system does not triage clinically and does not assess severity.

SEE PATIENT ACCESS →
03

Perimeter-Bound Orchestration

Models on infrastructure you control, designed so that Protected Health Information (PHI) does not leave your perimeter or reach a provider that could train on it. Built to GDPR Article 9-aligned controls, with access scoped by role and every record access logged.

SEE SECURE PIPELINES →
04

EHR System Workflows

Cross-platform workflows that bridge legacy Electronic Health Records (EHR) and modern clinical tools, so data is read, structured and routed across systems without replacing the EHR.

SEE CROSS-PLATFORM WORKFLOWS →
CONTROLS WE IMPLEMENT
GDPR ART. 9-ALIGNED CONTROLS PHI INSIDE YOUR PERIMETER NO TRAINING ON YOUR DATA ROLE-SCOPED ACCESS AUDIT LOG ON EVERY RECORD READ SOVEREIGN INFRASTRUCTURE

These are engineering controls we build into the architecture, not certifications. QQuantum.ai holds no security certifications, and the audits and attestations your sector requires remain yours to run — see our trust centre.

DESIGN TARGETS
0
PHI LEAVING YOUR PERIMETER
1+
CITATION PER EXTRACTED VALUE
100%
EXTRACTIONS TRACED TO A SOURCE PAGE

Properties we design and build to, not measured client outcomes.

HEALTHCARE USE CASES
QUESTIONS
QUESTIONS — 4

By architecture. Models run on infrastructure you control, designed so that patient data is not sent to public API endpoints and does not reach a provider that could train on it. Where a hosted model is used at all, it sits behind processor terms and a documented lawful basis, and the controls are enforced by the architecture rather than only by policy. Two limits worth stating plainly: the legal determination of whether those controls are sufficient for your context is yours to make, and if US health data is in scope, the HIPAA programme, the business-associate agreements and any attestation are yours — we hold none and cannot supply them.

Multimodal models read PDF trial reports directly — tables, charts and free text — and extract cohorts, adverse events and efficacy measures into a structured, reviewable form, with a source citation on every extracted value so a researcher can verify it. Adverse-event extraction feeds a human case assessment; it does not replace one. How much abstraction time this saves depends on your document set, which we measure on a sample before scoping.

Clinical triage is a clinical activity and in many jurisdictions a regulated one, so no. The patient-access systems we build handle scheduling, preparation and intake, and screen every contact for any indication of urgency before anything else — with the threshold set deliberately low. A contact touching symptoms, medication, deterioration or distress goes to a person immediately, with the full conversation attached. The system does not assess severity and does not advise.

Yes. We build cross-platform workflows that bridge legacy Electronic Health Records and modern clinical tools, so the system can read, structure and route data across them without a rip-and-replace of your existing EHR. That integration is usually the larger part of the build, and it is where the realistic timeline is set.

Keep reading
30-minute technical call · no deck

Return time
to care.

Start with an architecture review of your clinical and administrative workflows — the boundary comes first, then the build.

CASE STUDIES

Shipped work.
Go and check it.

The work we can name, with the live site, our scope and the boundary made explicit. Select a project to see the evidence; each is a full case study, not a logo or a claim.

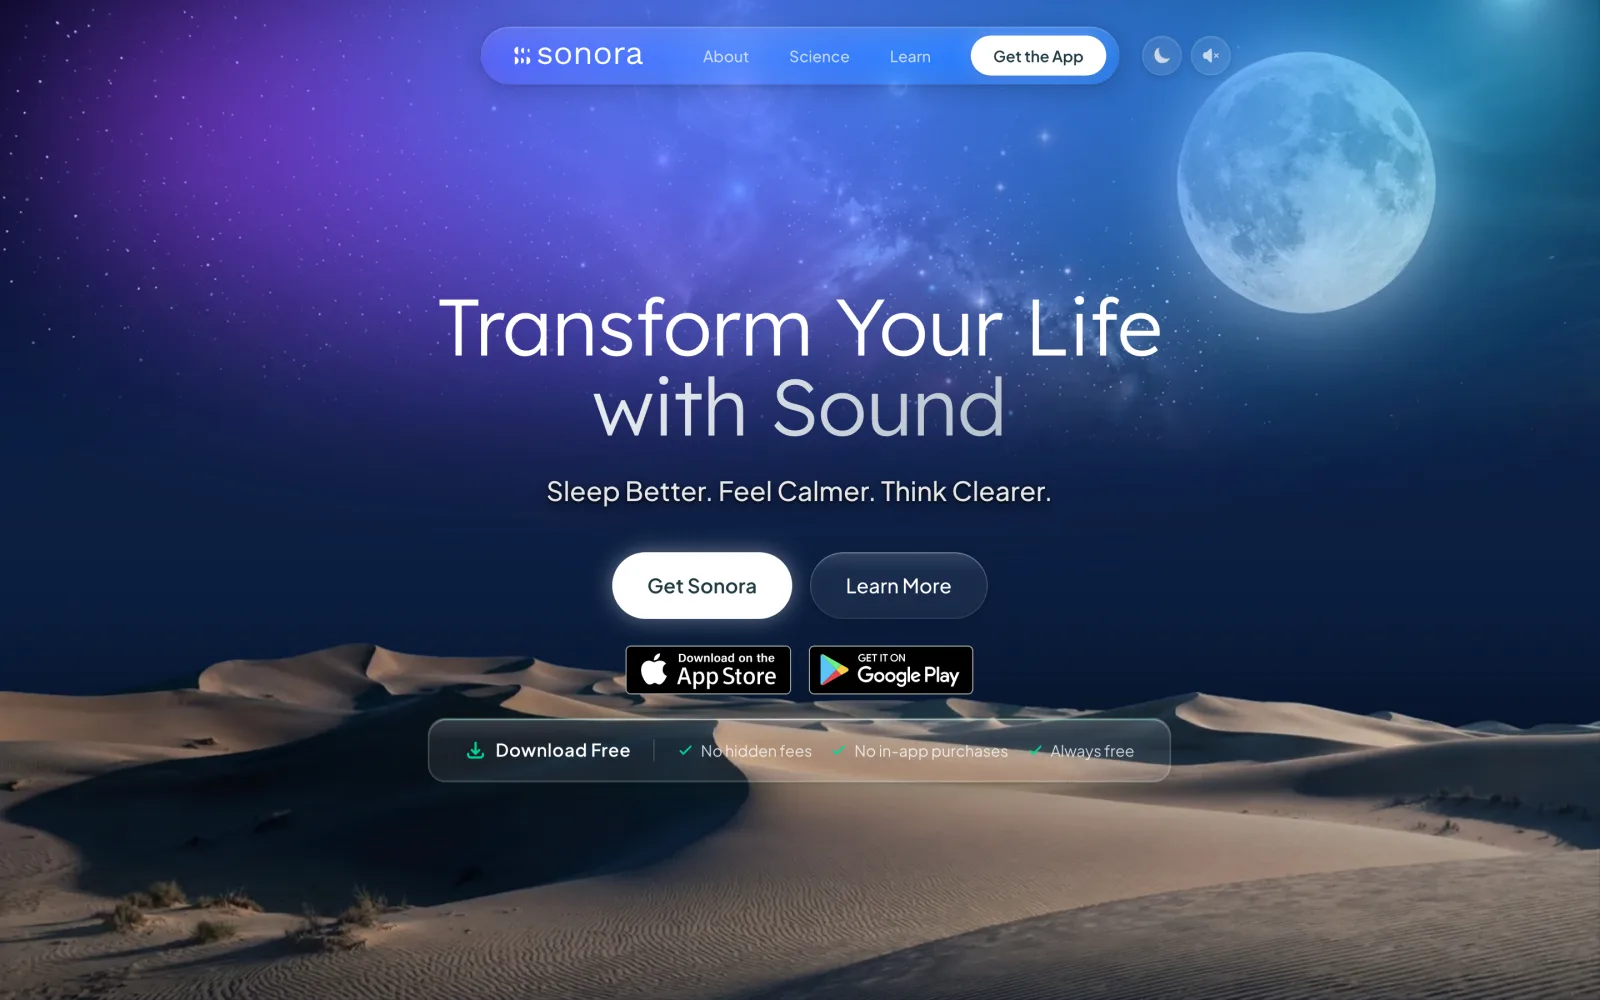
sonora.com
The Sonora homepage on desktop: a full-bleed dune landscape behind the headline “Transform Your Life with Sound”, with App Store and Google Play download buttons.
sonora.com — homepage, 1440×900 sonora.com →
Live Consumer wellness · Mobile + web

Sonora

Cognitive AI Ltd · 2026

A free sound-wellness app, described by its publisher as AI sound therapy that reads a short vocal sample at the start of a session and generates a soundscape for that moment. We designed and built the website and its backend, produced assets for the iOS and Android apps, and supported the application prototype.
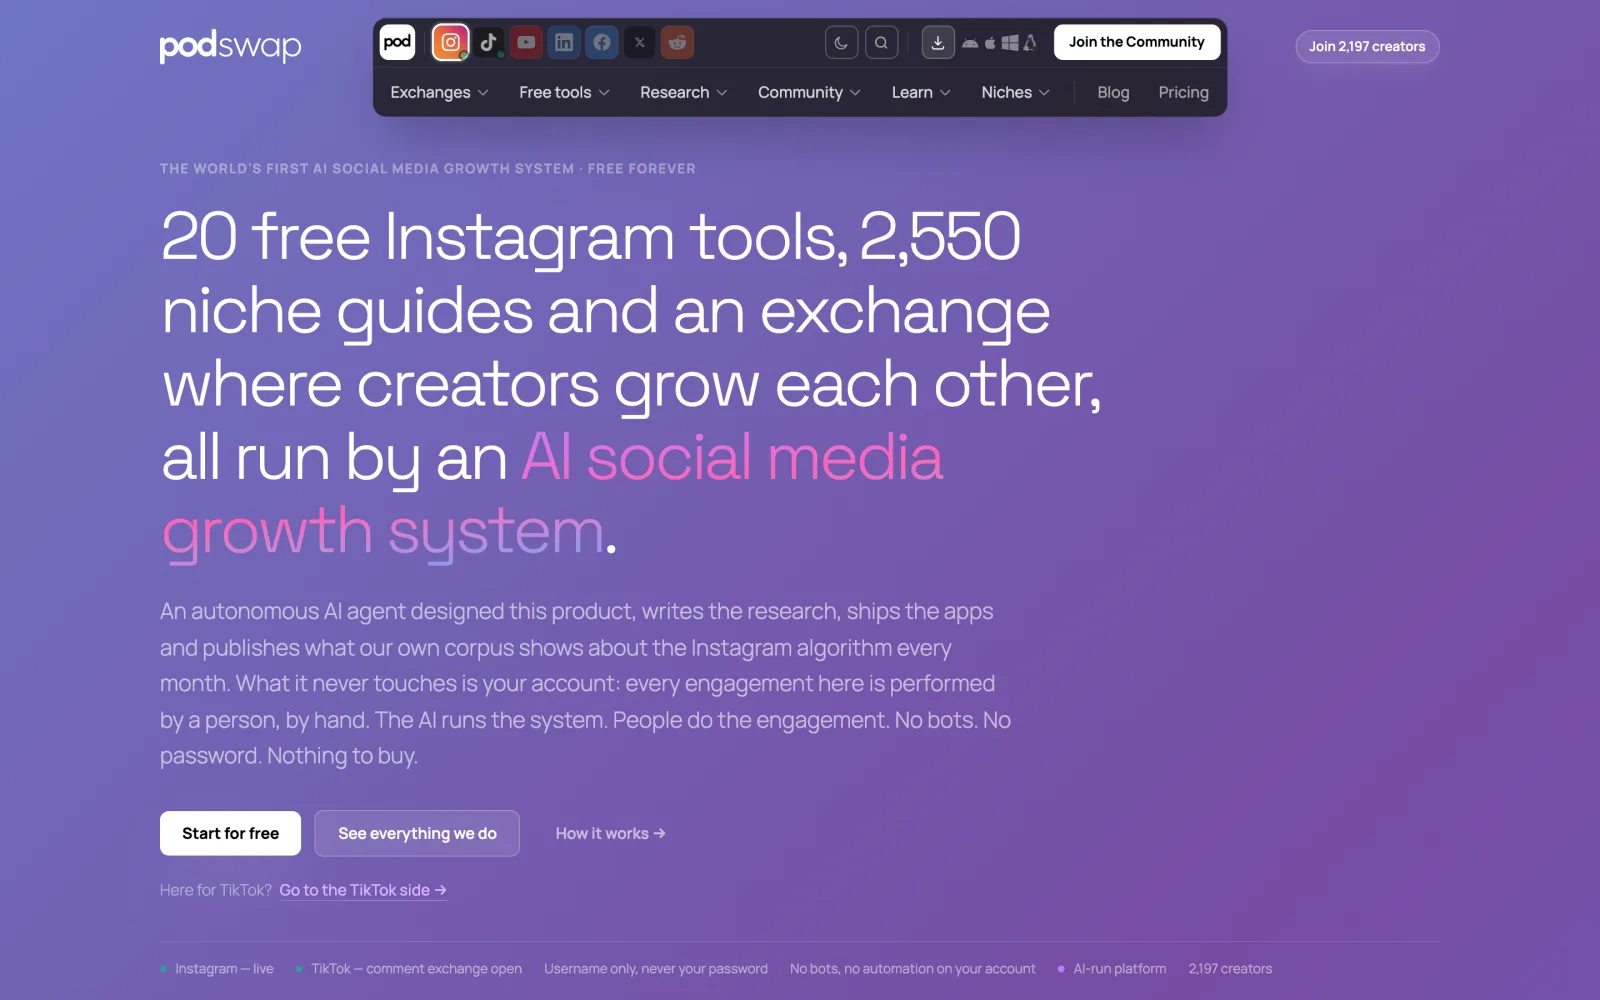
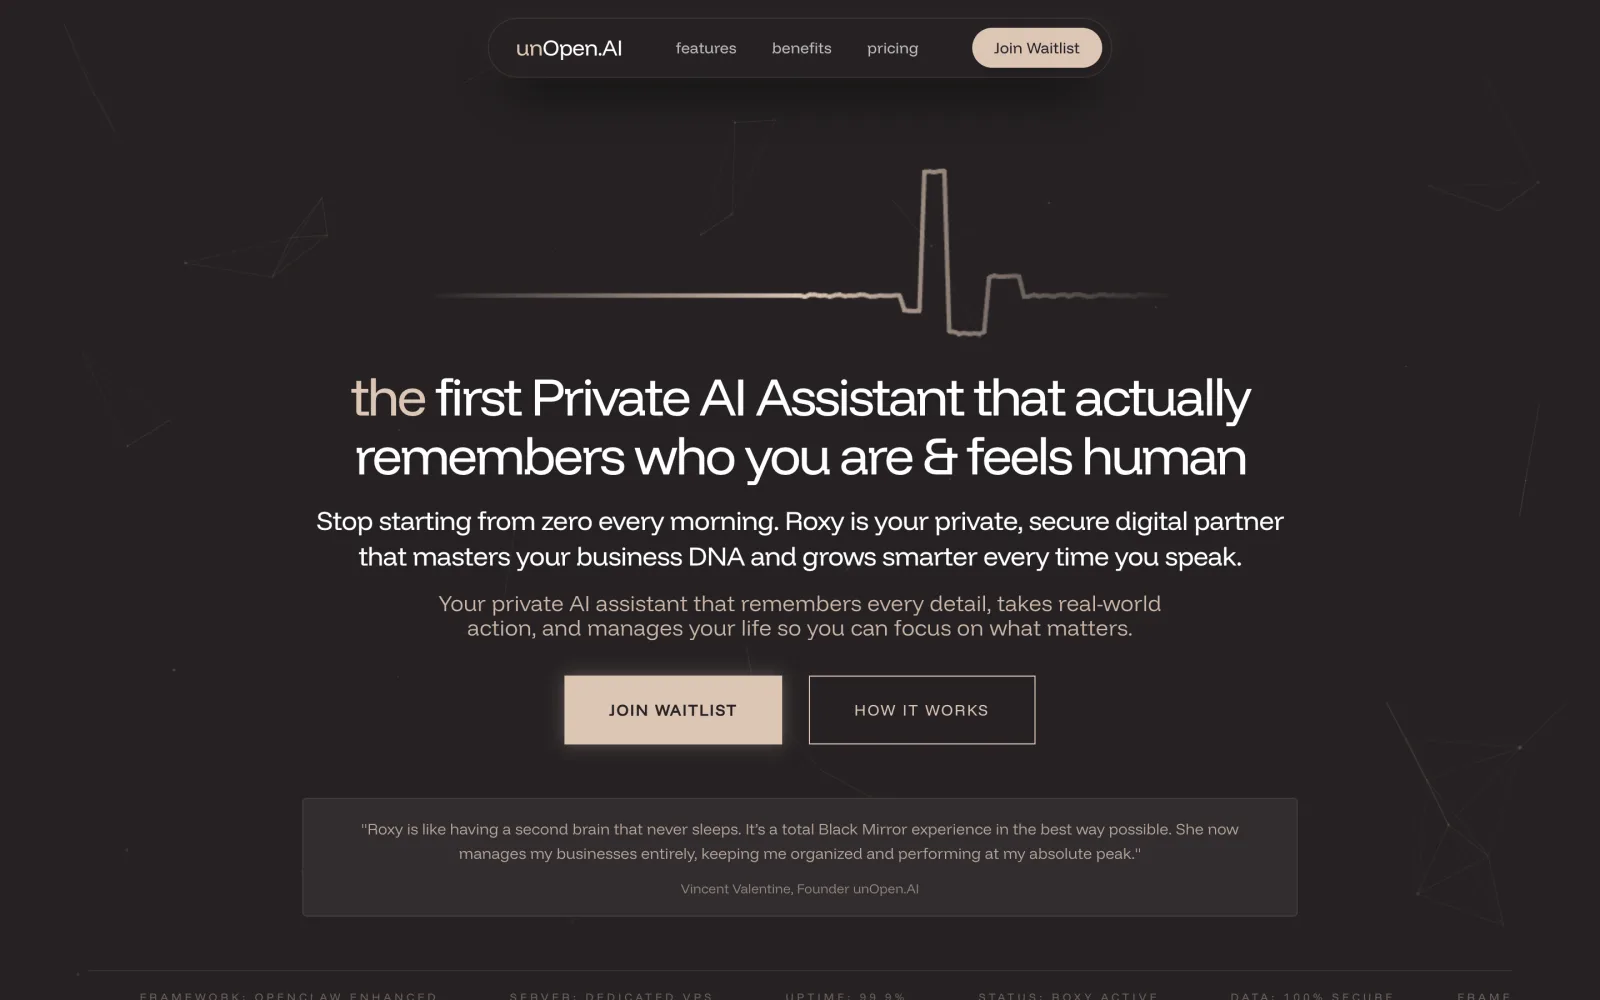
Read the case study →

See every published project →

WHO WE HAVE BUILT FOR

Twenty-one years of applications, platforms and campaigns for names you know.

See all of our work →



















